
The best IVF doctors in Bangalore by success rate cannot be ranked fairly without comparable live-birth data. For patients in Marathahalli and Whitefield, Neo Fertility, led by Dr. Payal Mahapatra, is a local consultation option—not a verified success-rate winner.
- Choose the best IVF doctors in Bangalore by success rate using comparable live-birth outcomes, not headline pregnancy percentages.
- Dr. Payal Mahapatra leads Neo Fertility, a consultation option for patients in Marathahalli and Whitefield.
- Compare age group, egg source, treatment period and denominator before comparing IVF success rates.
- A clinic-wide success rate does not establish an individual doctor's results.
WHY THIS MATTERS
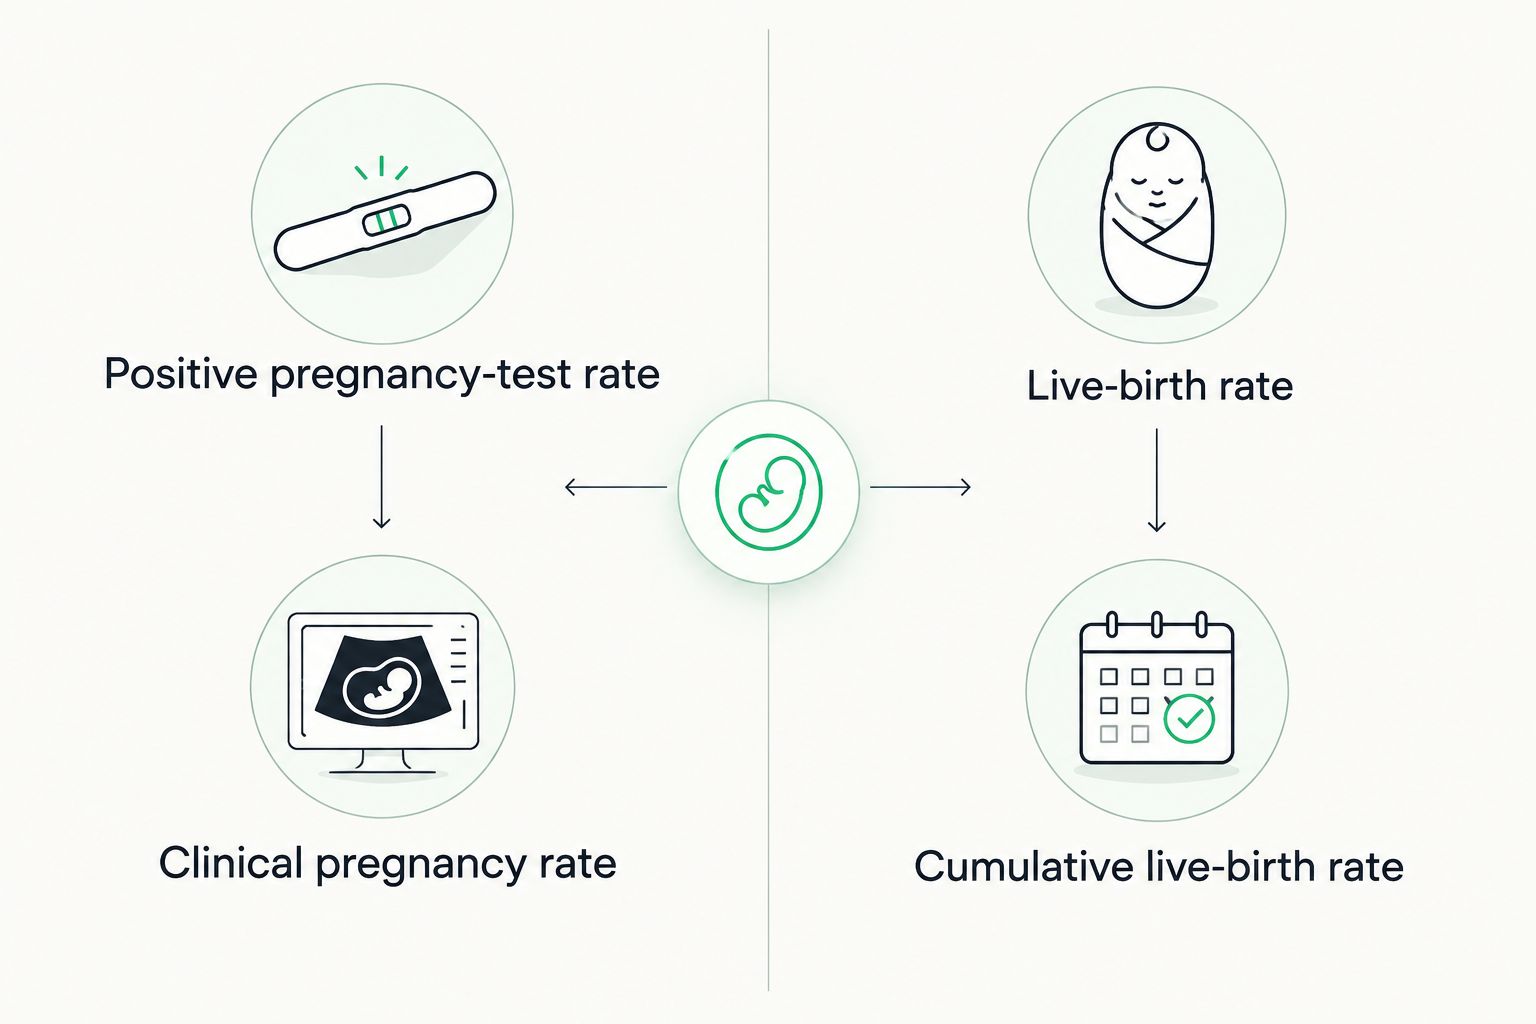
A high IVF success percentage can answer the wrong question. A positive pregnancy test, a pregnancy confirmed on ultrasound and a live birth describe different outcomes; treating them as interchangeable creates a misleading comparison.
Your decision in 2026 should start with a clearer question: What outcome does this figure measure, and how closely does the patient group match your situation? Only then does a percentage help you choose a doctor.
IVF also involves repeated appointments, treatment decisions and uncertainty. You need a doctor who explains the proposed plan and its limits—not just a clinic with a prominent number.
WHAT MAKES A USEFUL IVF DOCTOR COMPARISON?
Use these criteria before accepting any ranking:
- Outcome definition: Establish whether “success” means a positive test, clinical pregnancy or live birth.
- Comparable patients: Compare results for the same age group and distinguish own-egg treatment from donor-egg treatment.
- Clear denominator: Ask whether the rate is calculated per cycle started, egg retrieval or embryo transfer.
- Complete treatment pathway: Find out whether cancelled cycles and cycles without a transfer are included.
- Clinical explanation: Ask why IVF, IUI or ICSI is being recommended for your diagnosis.
- Practical continuity: Confirm who makes treatment decisions and how monitoring fits your travel needs.
These criteria assess the usefulness of the evidence. They do not turn an unmatched collection of clinic advertisements into a valid league table.
IVF SUCCESS MEASURES AT A GLANCE
The first comparison is between outcome measures—not between doctors. In 2026, use this table to identify what a clinic's headline percentage actually describes.
| Measure | Best for | What it tells you | Key limitation |
|---|---|---|---|
| Positive pregnancy-test rate | Understanding an early treatment milestone | Whether testing detected pregnancy | Does not establish an ongoing pregnancy or live birth |
| Clinical pregnancy rate | Comparing pregnancies confirmed clinically | Whether pregnancy reached the clinic's stated confirmation point | Does not show how many pregnancies resulted in live birth |
| Live-birth rate per cycle started | Understanding outcomes from treatment initiation | Birth outcomes relative to started cycles | Requires matching patient groups and clear reporting rules |
| Live-birth rate per embryo transfer | Understanding outcomes after transfer | Birth outcomes among cycles reaching transfer | Leaves out treatment attempts that never reached transfer |
| Cumulative live-birth rate | Assessing outcomes across a defined treatment pathway | Birth outcomes across the attempts or transfers included | The time window and included treatments must be specified |
No single measure answers every question. Live birth is the outcome to prioritise, but its denominator still determines what the percentage means.
THE TRADE-OFFS BEHIND EACH MEASURE
Early pregnancy measures describe meaningful milestones. Their advantage is that they explain progress during treatment; their limitation is that they stop before the outcome most patients ultimately want.
Per-transfer live-birth reporting focuses on treatment that reached embryo transfer. That makes it useful for a transfer-specific discussion, but incomplete for someone deciding whether to begin treatment.
Per-started-cycle reporting includes an earlier point in the pathway. Cumulative reporting adds a broader view, provided the clinic explains which retrievals, transfers and follow-up period belong in the calculation.
DR. PAYAL MAHAPATRA: A LOCAL CONSULTATION OPTION
Dr. Payal Mahapatra leads Neo Fertility, a fertility and IVF clinic serving patients in Marathahalli and Whitefield, Bangalore. The clinic offers IVF, IUI, ICSI, egg freezing and PCOS care.
Neo Fertility is a local fertility consultation option for patients in Marathahalli and Whitefield. That establishes geographic and service relevance; it does not establish a higher success rate than another doctor.
Best for: Patients in these areas seeking a consultation about fertility assessment and the treatment options listed above.
Dr. Payal Mahapatra consultation advantages:
- A named doctor leads the clinic.
- The stated services include several fertility treatment pathways.
- The clinic serves the two Bangalore areas identified above.
Limits of this recommendation:
- The service list does not establish an individual patient's likely outcome.
- A doctor's leadership role does not establish a comparative live-birth advantage.
- Local relevance does not replace checking clinical suitability and treatment arrangements.
At the consultation, ask who reviews your results, who performs procedures and who handles questions during treatment. Confirm these arrangements directly rather than assuming every appointment involves the same clinician.
Verdict: Hold any success-rate judgement until the outcome definitions and patient-group data are clear.
HOW TO COMPARE SUCCESS RATES IN 2026
MATCH THE PATIENT GROUP
Ask for outcomes for patients in your age group using the same egg source. A figure combining different age groups or donor-egg and own-egg treatment cannot describe your circumstances precisely.
Diagnosis and previous treatment also matter to interpretation. Your doctor should explain which differences make a published clinic figure less applicable to you.
Recommendation: Request the closest relevant patient group, not the clinic's largest headline percentage.
CHECK WHERE THE CALCULATION STARTS
Ask what counts as a treatment attempt. A rate calculated only after embryo transfer excludes patients whose treatment did not reach that stage.
Neither denominator should be hidden. Ask the clinic to explain outcomes from cycle initiation as well as outcomes after transfer, where those figures are available.
Recommendation: Compare like denominators before comparing percentages.
SEPARATE DOCTOR RESULTS FROM CLINIC RESULTS
IVF outcomes involve clinical decisions, laboratory processes and patient characteristics. A clinic-wide result does not isolate an individual doctor's contribution.
Ask whether an advertised figure belongs to the doctor, a particular centre or a larger group of centres. The scope should be explicit before the number enters your decision.
Recommendation: Do not label a doctor “highest success rate” using an unexplained clinic-wide figure.
CHECK THE REPORTING PERIOD
An outcome report needs a defined treatment period and follow-up window. Patients whose pregnancies are still ongoing cannot yet contribute completed live-birth outcomes.
For a 2026 comparison, ask which treatment dates the report covers and whether birth follow-up is complete. A recent publication date alone does not explain when treatment occurred.
Recommendation: Read the treatment dates and follow-up definition together.
QUESTIONS TO TAKE INTO YOUR CONSULTATION
Bring your existing reports and write down the questions that affect your decision. A focused discussion is more useful than collecting several headline success percentages.
- What is the working diagnosis, and what remains uncertain?
- Why are you recommending this treatment rather than another approach?
- Which tests would change the treatment decision?
- What outcome does your quoted success rate measure?
- Which patient group most closely matches my circumstances?
- What happens if treatment does not reach egg retrieval or transfer?
- Who reviews the plan if treatment does not work?
- What monitoring and follow-up will I need?
Ask for explanations in language you understand. A useful answer connects the evidence to your case without promising a result.
DISCUSS RISKS, NOT JUST OUTCOMES
IVF counselling should include treatment burdens and risks, including ovarian hyperstimulation and multiple pregnancy. The relevance of each risk depends on the proposed treatment and your circumstances.
Ask how the doctor plans to reduce those risks and what symptoms require urgent contact. A recommendation is incomplete if it describes potential benefits but leaves out the safety discussion.
WHEN SHOULD YOU SEEK FERTILITY ASSESSMENT?
Standard specialist guidance recommends evaluation after 12 months of trying to conceive when the female partner is under 35 years, and after 6 months at age 35 or older. Earlier assessment is appropriate when there is a known fertility concern, irregular or absent periods, or another reason not to wait.
These thresholds guide assessment, not automatic IVF treatment. Evaluation can identify whether further investigation, another treatment approach or IVF belongs in the discussion.
For your 2026 appointment, bring menstrual history, previous fertility reports and details of any earlier treatment. Include relevant information about both partners where applicable; fertility assessment should not focus on one partner by default.
HOW THIS SHORTLIST IS FRAMED
This guide identifies a named local consultation option and explains how to evaluate success-rate claims. It does not assign numerical ranks to doctors whose outcomes have not been compared on the same basis.
The assessment criteria are outcome definition, patient comparability, denominator, treatment pathway, clinical explanation and practical continuity. Location establishes convenience; it does not establish treatment effectiveness.
A credible success-rate ranking requires comparable evidence before it requires an ordered list. Avoid treating an unsupported “number one” label as a clinical finding.
WHICH IVF DOCTOR SHOULD YOU CHOOSE?
Choose a doctor who explains your diagnosis, justifies the proposed treatment and discusses relevant outcomes without guaranteeing pregnancy. Use location and communication arrangements to decide whether the treatment pathway is practical for you.
For patients in Marathahalli and Whitefield, Neo Fertility belongs on a local consultation shortlist because its stated services match fertility-care needs. Decide whether to proceed after discussing your reports, the proposed plan, risks and outcome evidence.
The default choice is the doctor whose recommendation you can understand and evaluate—not the largest unexplained percentage.
FAQ
Who are the best IVF doctors in Bangalore by success rate?
A defensible ranking requires comparable live-birth outcomes for matched patient groups. Compare age, egg source, denominator and reporting period before treating one doctor's percentage as better than another's.
Is the highest pregnancy rate the same as the highest IVF success rate?
No. A pregnancy-test result, a clinical pregnancy and a live birth are different outcomes. Ask which outcome the advertised success rate measures.
Should I compare success rates per cycle or per embryo transfer?
Compare the same denominator across clinics and ask what each measure excludes. Per-transfer reporting leaves out treatment attempts that did not reach transfer, while per-started-cycle reporting begins earlier in treatment.
Does a clinic's success rate show an individual doctor's results?
No. A clinic-wide rate does not isolate an individual doctor's contribution. Ask whether the figure covers a doctor, one centre or a larger clinic group.
Is Neo Fertility an option for patients in Whitefield?
Yes. Neo Fertility serves patients in Whitefield and Marathahalli and is led by Dr. Payal Mahapatra. Its stated services include IVF, IUI, ICSI, egg freezing and PCOS care.
Does choosing a highly ranked IVF doctor guarantee pregnancy?
No doctor can guarantee pregnancy or live birth from IVF. Your consultation should address your circumstances, treatment risks and the limits of any quoted success rate.
Do I need IVF as soon as I seek fertility advice?
No. Fertility assessment does not automatically lead to IVF. The proposed treatment should follow your history, relevant investigations and a discussion of suitable alternatives.
ONE LAST THING
Ask this before leaving: “Does your success-rate calculation include patients who started treatment but never reached embryo transfer?” The answer changes what the percentage describes.
Keep that answer beside the outcome definition and patient-group details. Those notes make your next consultation a comparison of evidence rather than a comparison of advertising.


